
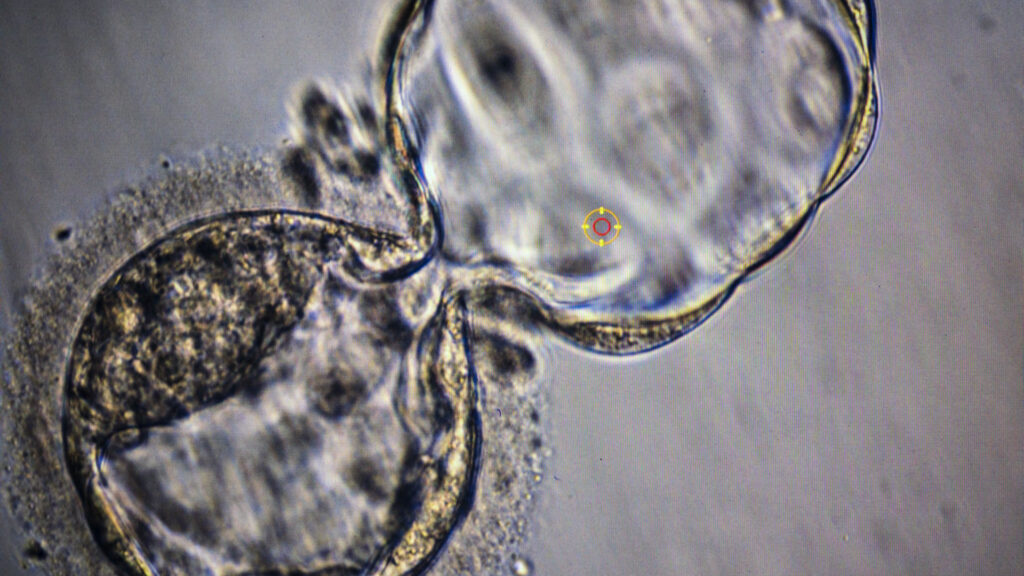
Highlights A pioneering IVF technique developed to reduce the risk of children inheriting sometimes-fatal mitochondrial diseases from their mothers is being marketed online as a fertility procedure for older women, despite scant evidence it works. The procedure, popularly called “three-parent IVF,” is illegal in the United States, but an Illinois-based company has facilitated a sprawling for-profit tourism industry, connecting women in the U.S. and Europe to clinics abroad. STAT’s investigation found examples of shoddy record keeping by a clinic providing the procedure, incomplete data published in marginal journals, and in one case, a puzzling ancestry test result that called into question the source of a child’s DNA. TIRANA, Albania — As you drive from the Tirana International Airport toward the heart of the Albanian capital, car dealerships and shopping center-lined freeways give way to tidy rows of Communist-era housing blocks, their concrete walls splashed in Funfetti-hued dazzle camo — reminders of the country’s darker periods hiding beneath a cheerful riot of cheap paint. Continue south and on your right, freshly laid roads snake up into hills dotted with luxury homes behind high white walls and security gates. Nestled among them, a red-bricked fertility clinic welcomes patients with a small courtyard and a sign emblazoned with the logo for the U.S. Food and Drug Administration. This is an “FDA registered facility,” it declares. When a Dutch woman named Wendy made this journey to the SAGA Clinic in February, she waited beneath a 3-foot fetus sculpted into the slate-colored wall of the spacious new lobby, before being led downstairs to a private room. From the exam chair she watched a grainy ultrasound image of her uterus as a doctor threaded in a catheter and gently deposited an embryo. She’d undergone this phase of in vitro fertilization, or IVF, a few times before. But this time the embryo wasn’t just a collection of cells carrying DNA from her and her partner back in the Netherlands. It also contained bits of genetic material from a third person, an egg donor from Ukraine. An embryologist named Birol Aydin had created the embryo using mitochondrial replacement techniques, or MRT. Also known as “three-parent IVF,” MRT is a controversial reproductive technology originally developed to spare children from being born with rare types of inherited diseases. But more recently, it has been marketed as a solution for age-related fertility issues, despite scant evidence of its safety or efficacy as an infertility treatment, and against the recommendations of professional medical organizations. The exterior of the SAGA Clinic features a sign with the FDA logo. An eight-month investigation by STAT found that over the past decade, hundreds of women have made similar pilgrimages — to clinics in Eastern Europe, Mexico, the Bahamas, the Philippines, and other countries whose permissive laws have fostered the emergence of a for-profit MRT tourism industry. Many of these women are in their late 40s or early 50s — driven by a fierce desire for a genetically related child and influenced by targeted marketing of MRT as a last resort option for unwinding biology’s cruel chronology. Wendy — who asked to go by her first name to protect her privacy — paid more than $30,000 for the procedure, which involved putting DNA from her and her partner into donated egg cells that had their nuclei removed. The idea, as she understood it, was that the younger eggs, filled with robust mitochondria — the energy factories of cells — would power each embryo through its stages of development, boosting the likelihood of a successful pregnancy. That’s how it had been advertised by the U.S. company she paid to arrange her treatments, the International Fertility Group of North America. Based outside Chicago, IFG is what’s known as a medical tourism facilitator, a sort of middleman that connects patients in countries where medical procedures are not available or not legal with doctors in countries where they are. Neither IFG nor its partner clinics that offer MRT have published data in reputable, peer-reviewed journals. For Wendy, this was a bit of a red flag. She knew it was a big gamble with a lot of money. “If I had the time I would have waited for the statistics to be published,” she said. But urgency pushed her forward. “In my case, I could not afford to wait. I was 46. It was now or never.” It’s difficult to know exactly how many babies have been born as a result of MRT, owing to a lack of transparency among the companies involved. Some fertility industry insiders estimate the number of births could be as high as 200. IFG, which recently emerged as one of the biggest players connecting women in Europe and the U.S. with clinics abroad, claims on its website that 34 babies had been born through its mitochondrial donation program as of February 2025, and that most of its patients are between the ages of 39 and 52. It also cites an eye-popping pregnancy success rate in excess of 50% for IVF cycles done with MRT, but offers no substantiation for this number. A company spokesperson declined to provide more recent birth figures or to provide pregnancy success rates broken down by age group. Research reviewed by STAT — including some never published — shows that MRT does not work for most older women, because their infertility is caused by factors other than worn out mitochondria. Several of the field’s top scientists described marketing by IFG and other clinics selling the technology to patients of advanced maternal age — 35 and older — as misleading and questioned the validity of their claims. The scant data presented at meetings lacks crucial information and claim birth rates so high they’re seemingly too good to be true, independent experts told STAT. Former clients of IFG, who came away from the experience without a child, now say they feel taken advantage of. Some, after paying thousands of dollars, decided to stop before going through with MRT, discouraged by the level of care and attention they received in clinics overseas. Others didn’t get any viable embryos from MRT. Or, like Wendy, the process failed after an embryo was transferred into the uterus. A few weeks after she returned home from Tirana for the last time, she took a pregnancy test. It was negative. Anecdotally, success stories seem few and far between. Aimee Eyvazzadeh, a highly sought fertility specialist in the Bay Area known as “The Egg Whisperer” to her fans, estimates that over the past three years, she has referred around 50 of her advanced maternal age patients to IFG and two clinics that perform MRT. “Unfortunately, I have not had a success story yet,” she said. “I wish that it was something that could give women a better chance than what we’re seeing right now.” But she remains hopeful about MRT and said she would still mention it to patients. In an emailed response to detailed questions, IFG emphasized that it is not itself a licensed medical clinic and does not perform medical procedures. “Patients considering innovative reproductive techniques should receive clear information about known risks, uncertainties, alternatives, and limitations before making decisions,” the statement said. “IFG does not characterize innovative treatment as guaranteed, routine, or risk-free. Patients are not promised a pregnancy, a live birth, or any particular outcome.” STAT’s investigation is based on interviews with 45 current and former patients, reproductive physicians and fertility clinic operators, and independent researchers studying MRT. Reporters also reviewed dozens of private Facebook group posts, WhatsApp messages, and other communications among women seeking MRT, as well as business filings, clinic licenses, and client contracts. While skepticism about IFG’s scientific claims has been previously reported by Nature, this investigation is the first to provide an inside look into the company’s operations and the experiences of its clients. STAT also is the first to report long-awaited data from the Ukrainian group that first offered MRT as a fertility treatment, and how the embryologist who pioneered it has tried for years, without much success, to alert patients and the scientific community to what he found: that MRT can’t liberate older women from biological reality. After STAT began making inquiries to IFG in July, the company posted an update to its website announcing a temporary pause on the acceptance of new MRT patients. In its statement, IFG said that this decision reflects the need to manage existing patients before further expansion and does not mean all activities associated with the program have ceased. “In a sensitive and evolving clinical area, it is preferable to proceed cautiously rather than prioritize volume,” the statement said. “Because the timing depends on independent clinical providers, their capacity, and their internal processes, IFG cannot provide a definitive date for when additional cases may be accepted.” Last week, following additional questions from STAT, IFG removed all mention of MRT from its website. In a statement, IFG said it has decided to suspend its MRT-related promotion, pending a comprehensive review, adding, “This is a precautionary communications decision, not a finding on the accuracy of each individual statement you have raised.” While some prominent scientists think that MRT may hold promise for addressing fertility challenges, they want to see it tested in rigorous research trials before being rolled out to patients. What’s happening now — families paying tens of thousands of dollars to participate in a poorly controlled intergenerational experiment, the results of which may never see the light of day — has physicians and ethicists worried about the financial exploitation of people desperate to be parents and the potential long-term consequences to the health of the children being born. “You’re paying for the privilege of being a guinea pig,” said Jeffrey Kahn, director of the John Hopkins Berman Institute of Bioethics. “Where else in medicine would people sign up for that?” From exhilaration to devastation On Christmas Day 2024, IFG posted to its Facebook page and Instagram account a list of 12 miracles to celebrate from that year. At No. 1 was the company’s introduction of mitochondrial donation, which the posts described as “a groundbreaking fertility treatment that offers renewed hope to women with advanced maternal age or a history of failed cycles.” An IFG Facebook post from December 2024 describes mitochondrial donation as a “miracle.” Since then, IFG’s social media posts have continued to target older women. “With age, egg ‘batteries’ lose power,” explained one. “MRT helps boost egg energy by adding healthy mitochondria, increasing the chances of healthy embryos.” One from January of this year, which opened with, “You’re 38 and still wondering if motherhood is possible?,” offered financial credits toward IVF or MRT services in exchange for sharing one’s patient story publicly. Another, from March, assures women over the age of 45 that it’s not too late to try MRT. (These posts and others were removed after STAT inquired about them.) A post from September 2025 on IFG’s Instagram page describes MRT as a way to “boost” the energy of older eggs. During an informational webinar IFG hosted in February, Aydin, the embryologist, was upfront that many factors can cause fertility issues in older women, and that a mitochondrial donation might not solve them. But even if something has only a 1% or 2% chance of working, he said, that’s often worth it, in his experience. “Of course, the science is not magic,” he said, “No one can make magic.” But if he were in their shoes, he told the more than 300 attendees, he would do everything possible to use his own DNA before moving to donated eggs, according to a recording of the webinar viewed by STAT. “They seem to portray it as if it’s established medicine and it is not,” said Heidi Mertes, a medical ethicist at Ghent University who specializes in assisted reproductive technologies and reviewed IFG’s website and other marketing materials for STAT. “There is no published study showing that any of this works for women above 40. … I think they’re really misleading patients.” IFG’s messaging appears to be working. A slide from the webinar showed that in 2022, the average age of a patient in IFG’s mitochondrial donation program was 39.2 years old. Last year, it was 45.6 years old. Wendy was 46 when she became an IFG client. She had spent most of her 30s in a relationship with a man who didn’t want children. She told herself their love was big enough to make up for not getting to be a mom. But as she neared her 38th birthday, her desire for motherhood won out. She left her boyfriend, and a few years later decided to embark on a co-parenting adventure with a close friend. She got pregnant quickly, conceiving naturally, and delivered a healthy baby girl. But when she started wanting a sibling for her daughter, Wendy struggled to conceive. And at 44, she was now too old to start IVF in the Netherlands and have it covered by insurance. After fertility procedures in Belgium and Spain failed, she turned to the internet, where she found a private Facebook support group for women who’d given up on traditional IVF but weren’t yet ready to move on to using donor eggs. Women swapped stories and resources about the science of MRT — comparing different methods, crowdsourcing pricing and statistics from different clinics, and trading information on which providers were actively taking patients. Wendy was exhilarated. “I wanted to know everything about it,” she said. “I was convinced that this was the road to getting pregnant with a baby with my genes.” Although the group is described as being devoted to MRT for fertility generally, most of the discussions revolved around IFG. One of its administrators claimed to be banking eggs through IFG for the purposes of doing MRT, and provided the group with a steady stream of updates regarding company policies or upcoming informational webinars hosted by IFG’s advisory clinical director, a Ukrainian fertility specialist named Uliana Dorofeyeva. Encouraged by these conversations, Wendy reached out to IFG for a free consultation. She said that over a 45-minute video call, Dorofeyeva reviewed her fertility history and told her she was a good candidate for the company’s mitochondrial donation program. Its details were laid out in the contract Wendy signed with IFG shortly after. For $20,000, she would get MRT performed on up to 15 of her embryos, with the first egg retrieval procedure included. The costs of the medications to stimulate her ovaries to produce eggs, the donor eggs they would be combined with, and genetic testing for any resulting embryos, were not. The contract explained that IFG’s role was to furnish a referral to a medical clinic for the treatment of fertility and provide support services coordinating those treatments. IFG clients seeking MRT also had to sign an informed consent form, attesting they had received “a full explanation regarding the nature, purpose and expected duration of the diagnostic and treatment process, as well as the potential risks and side effects that may arise during the course of treatment.” That consent form, stamped with IFG’s logo, stated that information regarding the proposed treatment methods “was provided by Dr. Uliana Dorofeyeva and the IFG-Contracted Healthcare Team.” After she put down a deposit, Wendy’s conversations moved to WhatsApp group texts with Dorofeyeva, Aydin, care coordinators from IFG, and staff at partner clinics. They provided her with a stimulation protocol and helped arrange her first egg retrieval in Tirana. Staff at the SAGA (Stem and Gene ART) Clinic there were only able to retrieve five eggs, so months later she flew back to Tirana for a second retrieval, and then to a different partner clinic in Georgia for a third. At the end of all that, she had 11 embryos to move forward with to MRT. In November 2025, Aydin performed the MRT procedure at the SAGA Clinic using fresh eggs retrieved from a donor flown in from Ukraine and fertilized with sperm from Wendy’s partner. Not long after, she received a message from Aydin that made her heart sink: Just two of her reconstructed embryos had survived to the stage where they could be transferred to her uterus. “I was devastated,” she told STAT. “I expected so much more.” She told Aydin as much, over text. “I was expecting more as well,” he replied. But, he wrote, there was no way to test the functioning of her mitochondria to determine whether they were the cause of her fertility struggles. “We are just assuming you may have mitochondrial issue and we are allowing you to try MRT,” he wrote. After one embryo turned out genetically abnormal and the other failed to implant, Wendy decided she’d had enough. She’d tried acupuncture, Reiki, osteopathy, energetic healing, praying to God, IVF, and now MRT. She’d spent her savings and weeks of her life crisscrossing Europe, waiting in airports, trains, taxis, buses, Airbnb rentals, and exam rooms. She was exhausted. Writing to the Facebook group’s 1,600 members earlier this year, she described her experience with IFG and announced that this was where their shared journey came to an end. “Most of you know that Dr. Mitalipov in Cyprus, stopped to treat woman above 45 years of age with MRT. There is a reason for this. We are too old. There will be exceptions, of course. But let’s face reality and the inconvenient truth, majority of us are too old and a pregnancy will never occur to us anymore. I am done. Good luck too you all.” An exterior view of the headquarters of International Fertility Group of North America in Northbrook, Ill. ‘How do we decide if it’s safe?’ On the wall outside Shoukhrat Mitalipov’s laboratory at Oregon Health & Science University, visitors are greeted by framed portraits of furry scientific celebrities. Among them are a pair of rhesus macaque twins — Mito and Tracker— the first primates born from eggs made via a form of MRT called spindle transfer. When their births were announced in the pages of Nature in August 2009, it made international headlines and established Mitalipov as one of the world’s foremost experts in genetically manipulating egg cells. The spindle transfer method he pioneered involves performing microsurgery on the oocyte, or egg cell, as it is in the process of meiosis, or separating and shedding half of its chromosomes in preparation for the possibility of running into a sperm. During meiosis, a structure called the spindle forms, which lines the chromosomes up and eventually pulls them apart. The spindle can only be visualized with a special kind of microscope that emits a beam of polarized light. As it passes through the spindle’s tightly aligned microtubule fibers, the light splits, showing Mitalipov where to insert the micropipette that will suck the spindle out of the egg. What’s left is a bunch of goo — technically termed cytoplasm — and all the things suspended in it that are there to help the egg, once fertilized, successfully divide and begin developing into an embryo. They include tiny bits of RNA and proteins involved in gene expression, as well as hundreds of thousands of mitochondria, each with their own circular genome. Into this empty egg a spindle from another animal is then inserted, the reconstructed egg finishes its process of chromosome halving, and is then fertilized. How maternal spindle transfer works: 1. Nuclear DNA from the patient’s egg (blue) is extracted and placed into a donor egg (orange) that has had its own nuclear DNA removed but retains its mitochondria. 2. The newly created cell is fertilized by sperm and transferred into the patient’s womb. 3. The resulting baby has nuclear DNA from both parents and mitochondrial DNA from the egg donor. After the successful births of Mito, Tracker, and three other monkeys via spindle transfer, Mitalipov petitioned the FDA to let him try his technique in humans, as a way to help women who carry rare mutations in their mitochondrial DNA have genetically related children, without passing on their own glitchy mitochondria. But before the agency could give the go-ahead, Congress adopted a spending bill into which anti-abortion Republican lawmakers had slipped a one-sentence rider forbidding the FDA from even acknowledging “receipt of a submission” of any proposed clinical trial in which a human embryo was modified, let alone approve one. Despite efforts since then to reverse the ban, MRT remains effectively illegal in the U.S. to this day. From the beginning, MRT has been the subject of ethical controversy because of the unknown health risks of exposing unborn children to any amount of donor DNA. Such risks would be carefully explained to any potential research subjects participating in a clinical trial or a strictly regulated process, as in the U.K., where an independent panel of experts approve MRT on a case-by-case basis. So far, the U.K. health authority has permitted only one clinic, at Newcastle University — where a different form of MRT called pronuclear transfer was pioneered — to perform the procedure, and only for the purposes of preventing mitochondrial disease. But in an unregulated commercial setting, such risks are more easily downplayed, which raises the ethical concerns, experts told STAT. Part of the problem, which is somewhat unique to MRT, said Kahn, the Johns Hopkins bioethicist, is that scientists and ethicists are perplexed about how to establish its safety. Is it just a baby born, is that the threshold? Or do you need to know something about any impacts of donor DNA on the health or reproductive potential of the adult that baby becomes? Getting that kind of data would mean waiting 20 years or more. “How do we decide if it’s safe, and what does safety mean in this context?” Kahn said. “It’s very complicated.” It’s something the FDA was preparing to weigh in on, back before Congress forbade it from doing so in 2015. It would have been the first time the agency’s reach would have extended to regulating an assisted reproductive technology. Kahn sees this as a missed opportunity to course-correct the entire IVF industry, which, cut off from federal research dollars by religious conservatives’ opposition, has grown up in the U.S. as a consumer good for those with deep enough pockets to access it on a lucrative private market. Light regulation has led to the proliferation of dozens of supplementary procedures, IVF “add-ons” that purportedly increase the odds of having a baby, though several large meta-studies have found the science underlying these add-ons to be shaky. That MRT is being marketed as just another one of these add-ons by clinics outside the U.S. is a predictable consequence of the congressional ban, Kahn said. “When there’s a prohibition here, then people find other places to go. And if there’s a business model, then someone’s going to set up shop in a place with less regulation or, you know, no regulation at all.” MRT becomes a fertility therapy Tirana is such a place, where medical tourism — for hair transplants, rhinoplasties, dental surgeries, and other procedures — is big business. Patients might think the sign with the FDA seal outside the SAGA Clinic means it is regulated or inspected by the agency, but it merely means SAGA is registered with the FDA’s database of establishments that manufacture human cells for import into or export out of the United States. This does not mean that a clinic or company is licensed or approved by the FDA, an agency spokesperson told STAT in an email. “Patients and consumers should not interpret registration alone as a measure of product safety, quality, or FDA endorsement,” they wrote. Kyiv is another place with lax government rules. It’s where, more than a decade ago, a Ukrainian embryologist named Pavlo Mazur began developing pronuclear transfer not for preventing mitochondrial disease, but as a potential infertility treatment. In the spring of 2016, he performed the procedure — which involves swapping DNA after fertilization rather than before — on embryos from two women who’d struggled for years with IVF. For the first time, their embryos developed normally and they got pregnant. Mazur’s boss, Valery Zukin, the director of the Nadiya Clinic, had intended to wait until they gave birth to tell the world. But then they got scooped. How pronuclear transfer works: 1. The patient’s egg (blue) is fertilized by sperm to create an embryo. 2. Nuclear DNA from a donor embryo (orange), fertilized by sperm from the same man, is removed and discarded, leaving behind mitochondria, and the parents’ nuclear DNA is inserted into the donor embryo. 3. The resulting baby has nuclear DNA from both parents and mitochondrial DNA from the egg donor. In September 2016, reproductive endocrinologist John Zhang and his team at New Hope Fertility in New York City announced the birth in Mexico of an apparently healthy baby using spindle transfer. The mother carried an error in her mitochondrial DNA that had proven fatal to her first two children. In 2017, Zhang and Zukin teamed up to form a new company, Darwin Life-Nadiya, to market pronuclear transfer to women struggling with infertility and willing to travel to Ukraine and pay between $8,000 and $15,000 for the procedure. To Mazur’s dismay, many of the patients Zhang recruited were women of advanced maternal age, who had been told that pronuclear transfer might be able to counteract something that happens to women’s eggs as they age: The process of meiosis becomes more error-prone. Chromosomes can get lost, or stick around when they shouldn’t — resulting in embryos with an abnormal number, a condition called aneuploidy. Rates of aneuploidy rise steadily throughout the 30s, then spike sharply after 40. In his experience with Ukrainian couples up to that point, Mazur had not seen pronuclear transfer do much to reverse those trends. But Zukin and Zhang wanted to keep trying. So over the next two years, Mazur and his labmate Lada Dyachenko performed pronuclear transfer on hundreds of zygotes from dozens of infertile patients, including 19 women between the ages of 36 and 44. Within that group of advanced maternal age patients, only one, a 42-year old, ever obtained a single embryo with the correct number of chromosomes. She delivered a healthy baby boy in 2018. The disappointing results confirmed what Mazur had suspected: For most women of advanced maternal age, the nuclear DNA inside their egg cells is damaged, and swapping it into a younger egg won’t change that. “It’s too late to make a difference,” he said. Embryologist Pavlo Mazur in a laboratory of the Nadiya Clinic in Kyiv, Ukraine, in 2017. And he had further proof. For some of his older patients, rather than discarding their eggs after the nuclear DNA had been removed, he ran an experiment in which he swapped into them the leftover nuclear DNA from the young donors. The results were surprisingly good. From these reverse reconstructed eggs, 40% of the ensuing embryos developed to the stage where they could be implanted; of those, 70% had a normal number of chromosomes. In other words, the older women’s mitochondria weren’t the problem. Mazur wrote up these results and submitted them to the American Society for Reproductive Medicine. Only after his poster was accepted did he let Zukin and Zhang know. They were furious, Mazur recalled, accusing him of setting a trap to force them to abandon the lucrative project. Reproductive endocrinologist John Zhang speaks at the American Society for Reproductive Medicine’s annual meeting in 2003 in San Antonio, Texas. Which wasn’t exactly wrong, he said. Performing the protocols was exhausting work, filled with long nights in the lab for which he and Dyachenko weren’t well compensated, and he was tired of doing it when the clinic had enough data to show clearly that it wasn’t effective for older women. But more importantly, he wanted the science out there. In October 2019, Mazur flew to Philadelphia to present the poster at the annual ASRM meeting. After that, Zhang’s team stopped sending frozen patient eggs to Ukraine. Two years after it started, Darwin-Life Nadiya was done. Ten babies had been born from pronuclear transfers, nine of them to mothers who were 35 or younger. Zukin said in a recent interview that it remains an “open question” whether MRT helps with aneuploidy in older women, but that he is transparent with potential patients at his own clinic that its odds of success are very low. Wanting to get the data in front of a bigger audience, Mazur collected the results into a manuscript. Journal after journal rejected it because Mazur hadn’t obtained consent from patients whose leftover eggs he used, nor permission from an ethics board to conduct his experiments. (The manuscript and the ASRM poster were shared with STAT.) “It’s in a way a minor problem in the bigger picture, but you absolutely do need to get a permit for that,” said Jacques Cohen, a New York-based embryologist and former editor-in-chief of Reproductive Biomedicine Online. Cohen told STAT that if he’d still been in charge, he might have elected to publish the manuscript alongside a commentary criticizing the ethical elements of the work. “It’s really sad,” Cohen said. “Because their work is important. It’s an incredible loss for the field and the public and the patients that they’re missing out on this information.” For fertility entrepreneurs, though, this void left a business opportunity. Fleeing Kyiv with a car full of eggs and embryos In 2017, a Ukrainian fertility clinic called IVMED, just a few blocks from the Nadiya clinic in Kyiv, hired a laboratory director to help it get in the MRT game. It was Aydin, who grew up in Turkey, where he studied biology and trained as an embryologist, and who would later perform the procedure for Wendy and other IFG clients. Slightly built, with shoulder-length black hair, hawkish features, and delicate hands, he had previously learned how to perform a related procedure — cloning — with cow embryos, and now adapted his skills to pronuclear transfer with human embryos. At first, Aydin told STAT, he worked exclusively with patients carrying mitochondrial DNA mutations. It was just a handful, maybe half a dozen, but many of them were over 40. As he watched these women’s reconstructed embryos developing through a microscope, he noticed that they looked healthier — smoother and more symmetrical — than embryos he typically saw from women of that age. Then other scientists published a study in mice suggesting pronuclear transfer could address poor embryo development associated with age. “This was where the idea came from … that it can be used for advanced maternal age,” Aydin said. He began presenting data at meetings in Ukraine suggesting MRT could help older women increase their odds of pregnancy, but by that time, Mazur had already seen enough to give up on the idea. Both men said they were friendly back then. Mazur describes Aydin as open and personable, a “good guy.” But he was mystified as to how Aydin was achieving much better outcomes. Their local rivalry might have continued if not for Russia launching its invasion of Ukraine and changing the trajectories of both their lives. In February 2022, as missiles rained down on Kyiv, Aydin loaded his car with steel tanks filled with IVMED patients’ frozen eggs, sperm, and embryos and shuttled them out of the country and to a safe harbor in Slovakia. For days, Mazur was pinned down in his home on the west bank of the Dnieper River with his wife and children, unable to reach the Nadiya clinic, which amid the chaos paused operations. Later that spring, when Aydin briefly returned to Kyiv, he hired Mazur to take over the MRT cases from him at IVMED. It made sense. “He’s the pioneer,” Aydin said. Plus, Aydin had a new opportunity — to run the lab at Ovogene, an egg, sperm, and embryo donor bank Dorofeyeva, the fertility doctor, whom he’d met in Kyiv, was opening in Slovakia to escape the war. As Mazur combed through his predecessor’s records, he didn’t see the kinds of things he had tracked in his own lab — dates of procedures and detailed outcomes for each patient along with information about their histories and donors. “It was just a random table with random numbers without even IDs of patients,” Mazur said. The following year, a similar-looking table appeared in The Journal of Reproduction, claiming that in a group of 27 advanced maternal age patients, MRT had led to an average live birth rate of 48.3%, with a 33% live birth rate for women over 42 years old. If true, this would be a significant improvement over traditional fertility procedures. According to one of the largest studies of IVF outcomes in women 45 and older, the live birth rate was 4.4% per embryo transfer. The study, co-authored by Aydin and Dorofeyeva, also claimed it was the first demonstration that MRT lowered aneuploidy rates, irrespective of age. “This is likely due to the highly functional donor mitochondria providing sufficient energy,” they wrote. However, they did not present any data showing that the resulting offspring did in fact have high levels of donor mitochondria. Scientists who reviewed the study at STAT’s request pointed to a number of oddities that raise questions about how it came to be published, including that it was accepted for publication less than three weeks after it was submitted and that Dorofeyeva was a member of the journal’s editorial board. The study appeared alongside a full-page ad for Aydin and Dorofeyeva’s egg-banking company, Ovogene, which provides the donor eggs for IFG’s mitochondrial donation clients. The Journal of Reproduction, which was launched in January 2022 by Ricardo Asch Schuff — an Argentinian obstetrician who fled the U.S. in 1995 amid allegations of fertility fraud — is not indexed in any of the major medical journal repositories. Aydin defended the integrity of his data. But he also said that collective statistics — even stratified by age — aren’t a good representation of MRT’s effectiveness as a fertility treatment because there are so many confounding variables in patient histories and differences in egg freezing and culture conditions among clinics. “You cannot put yourself into the statistics as a patient,” Aydin said. Mazur, who left IVMED in 2025 and now runs an early-stage startup developing artificial intelligence for improving IVF embryo selection, said he’s speaking out now because he’s seen the growth of clinics offering MRT targeted at older women. “After I started this, there were a lot of parasites trying to just convert these techniques into some commercial things to just take money from patients and to promise nothing,” he said. He’s been troubled to see more reputable venues conferring legitimacy on these commercial MRT operations. One example is a conference abstract for a 2025 meeting of the European Society for Human Reproduction and Embryology — a group that opposes MRT as a commercial fertility treatment and recommends it only be used with strict research protocols that guarantee the long-term follow-up of any resulting offspring, given that “the safety of nuclear transfer cannot be established.” In the abstract, Aydin and Dorofeyeva reported live birth rates of 40% or higher for IVF plus MRT among 66 patients with a mean age of 39. Its title declared that MRT “effectively enhances embryo quality and pregnancy outcomes in patients with advanced maternal age and diminished ovarian reserve.” The abstract was accepted though other scientists told STAT it lacked key information required to support such claims — including how many women were in each age group and how many IVF cycles each patient went through. Conference abstracts are typically screened for things like novelty and impact, but they’re not peer-reviewed in any deep or meaningful way. “I didn’t see this abstract, but I would have had serious reservations about including it,” said the former chair of the ESHRE executive committee, Karen Sermon, a professor of genetics and embryology at Vrije Universiteit Brussel in Belgium. Dieter Egli, a stem cell biologist at Columbia University, has pushed the U.S. to relax its ban on MRT for patients with mitochondrial disease, but he doesn’t support its use for improving fertility. “The science is just not sound enough,” he said. “It’s clearly not something that I would consider the right thing to provide to patients.” To date, there’s only been one published peer-reviewed study of mitochondrial donation for overcoming infertility, from Mitalipov and his collaborator Nuno Costa-Borges. In 2023, they published data from a study at a fertility clinic in Greece, reporting that spindle transfer resulted in a 31.6% live birth rate per transfer in a group of 25 patients under the age of 40. But a breakdown by patient age, buried in the supplemental material, shows that for 12 patients who were age 39, the live birth rate was less than 10%. “It was obviously successful for the younger group, but for the older group much less so,” said Mary Herbert, a reproductive endocrinologist at Monash University in Melbourne. (Mitalipov told STAT that he thinks MRT is unlikely to work for women over the age of 40, but has not yet been able to test that.) Herbert is a pioneer of MRT herself; she was one of the leaders of the research team at Newcastle University that performed the first such procedures in the U.K. and is now gearing up to launch a clinical trial in Australia, for the prevention of mitochondrial disease. In recent months, she has been scouring the scientific literature for evidence of the technology’s efficacy for treating age-related ovarian infertility, as part of a review on the topic she’s been asked to write for Nature Medicine. “The idea that mitochondrial dysfunction contributes to the age effect seems to have gained a lot of currency in the field,” Herbert told STAT. “But the actual direct evidence for that is very, very sparse. I would say I’m still looking for it.” ‘Was I lied to?’ Despite IFG’s claims about MRT in women of advanced maternal age, its online presence is notably lacking first-person testimonials from these clients. Since the official launch of its mitochondrial donation program, the person most frequently featured is Heidy Willis — a lawyer born and raised in Miami — and her husband, Josh. The couple had struggled for years to build the family they wanted, and round after round of IVF had failed in the United States. After pursuing MRT in Albania, Willis gave birth to healthy identical twin girls. Posts and videos detailing her story are not tagged with #advancedmaternalage, as are some other posts, but they fail to mention that Willis had just turned 33 when she delivered her daughters, and that a second step done alongside MRT could have contributed to her success. Willis’ fertility struggles had started when she was in her 20s. In an interview, she told STAT that every time she did IVF she would produce dozens of eggs, upwards of 30 or 40, but none would mature, baffling one doctor after another. She eventually underwent testing that found mutations in two genes on chromosome 10 associated with fertility issues, including arrested egg maturation. “So that’s when I started looking to see what can you do, and this mitochondrial replacement therapy thing came up,” Willis said. She tried the clinic in Mexico where Zhang’s first baby had been born, but was told they were no longer offering MRT for legal reasons, Willis recalled. She was also turned down by Mitalipov, whose study of spindle transfer at a Greek clinic was full. Zukin told her she could get MRT at the Nadiya clinic, but she wanted to have multiple children and worried he might retire. She felt more confident in Aydin, the embryologist at IVMED, whom she’d found online. He was young and described MRT in more assured terms. “We’ve seen this before,” she recalled him telling her. “I think we could solve your issue.” One of the laboratories of the Kyiv-based Nadiya fertility clinic. Aydin had an old friend who ran a hospital in Albania, and that’s where the Willises went to have Heidy’s eggs retrieved. She got about 30, and like all the other times, they were immature. So Aydin first did a separate procedure called in-vitro maturation, feeding the eggs a specialized culture with additional hormones to prod them to mature, followed by MRT. The Willises were left with one reconstructed embryo that appeared genetically normal. That’s the one they transferred, and which would later split inside Willis’ womb. The couple has described the girls as the world’s first MRT twins. But Aydin, speaking to STAT, said he can’t be sure whether it was the maturation step or the MRT that was responsible for the successful pregnancy. “I cannot say that mitochondrial transfer help,” he said. There was something else. Not long after the twins were born, Willis had momentary doubts about the procedure. They arrived in an email, from 23andMe, with results of genetic tests on DNA from her daughters that Willis and her husband had sent to the company out of curiosity. They had thought it would show a little bit of Ukrainian ancestry from the egg donor, maybe up to 10%. Instead, the report estimated the girls had 50% Ukrainian ancestry. Willis’ mind began to race; “Was this just a donor egg? Was I lied to?” she recalled thinking. Had the clinic not performed MRT? Upset, she reached out to Aydin and Dorofeyeva. She said they assured her that was to be expected; that tests like 23andMe calculated ancestry estimates from mitochondrial DNA, and her children had inherited all their mitochondrial DNA from the Ukrainian egg donor. 23andMe disputed this characterization, telling STAT that the company’s ancestry composition reports are built by analyzing hundreds of thousands of bits of DNA captured across a person’s chromosomes, housed in the nucleus. The reports do not include mitochondrial DNA, the company said. When asked about this, Aydin pointed out that 23andMe is not a diagnostic test and chalked it up to a lack of precision on the part of consumer DNA testing products. When he took an ancestry test, he said, it showed him having Italian roots, “but we don’t have any connection with Italy.” As for Willis, she told STAT that she doesn’t intend to pursue the issue further. “After all this, I don’t care if they’re mine,” she said. “I’m just happy to be a mom, you know?” She remains confident in MRT — she returned to Albania to do it again, resulting in the birth of a son. And she worries that any negative media attention on the clinics providing MRT or their doctors might keep other women, “some of whom are pursuing it as their last hope,” from getting that same opportunity. Patient eggs, sperm, and embryos are stored inside liquid nitrogen-filled containers at the SAGA Clinic. A tangled web of companies and family ties Hoping to get answers about IFG’s operations, a STAT reporter went to its headquarters, located in a low-slung brick office complex in Northbrook, Ill., an affluent lakeshore suburb of Chicago. We found a tangled web of companies whose principals have extensive family ties. At the center of it all is Dorofeyeva. On an afternoon in late July, two women stood huddled behind a bright white front desk at one end of its semi-finished lobby. At the other end, plastic-wrapped furniture lay in piles, beyond which was a dark corridor lined with empty offices. From a dimly lit conference room emerged a third woman, tall and blond, with a Ukrainian accent who identified herself only by her first name, Anna. They all appeared surprised to have a visitor. Since she was only a consultant for IFG, Anna explained, she couldn’t answer any questions about the company or its MRT program. She emphasized that IFG was not a clinic, but a patient services coordinator, and that MRT is illegal in the U.S. Someone from the company would be in touch, she said. That person was Ruslan Chervak, who identified himself in a brief phone call as IFG’s marketing manager. He told STAT that Dorofeyeva isn’t an IFG employee and that she serves in an advisory role. Regardless of the legal distinction, to patients, Dorofeyeva is the face of IFG’s mitochondrial donation program. Corporate registration records reviewed by STAT in the U.S., Slovakia, and Albania also suggest her connections with the company and its contractors may run deeper. In 2023, International Fertility Group of North America was incorporated in the state of Illinois, by a man named Igor Kostyuk. IFG said in a statement that he serves as its president. Illinois records indicate that Kostyuk also incorporated Ovogene in 2021, and Ark Cryo — which ships frozen eggs, embryos, and other biomaterials internationally via human courier — in 2020. Companies with nearly identical names were later incorporated in Slovakia, where business records list Dorofeyeva as the sole or co-owner. At the Slovakian Ovogene, she shares control with Yuliya Mazepa, whose son Ostap Mazepa variously describes himself on social media as Ovogene’s CEO and chief commercial officer. He is married to the chief operating officer of IFG, Maria Mazepa, and his father is Ruslan Chervak. On its website, Ovogene lists two locations, one in Slovakia and the other in Northbrook, Ill. — at the same address as IFG. (Neither Ovogene nor the Mazepas responded to STAT’s questions.) In addition to her role in these companies, Dorofeyeva owns a stake in the SAGA Clinic in Albania, along with Aydin and Ahmet Kal, the Turkish co-founder of the hospital where Willis underwent her first MRT procedure. In a statement, IFG said that it has no legal relationship with the Slovak company with the nearly identical name that is owned by Dorofeyeva, nor does it hold ownership interests in either of the other Slovak companies. Although it did not deny a familial link between the U.S.-based and Slovak-based entities, IFG said “a family relationship does not, however, by itself establish common corporate control, a conflict of interest, or improper conduct.” The statement added that commercial cooperation is not unusual in the fertility industry, where patients may require multiple specialized services across jurisdictions and that “each entity maintains its own corporate structure, management responsibilities, accounting, contractual obligations, and regulatory requirements.” Dorofeyeva told STAT she has no ties to IFG other than being a paid consultant. The separate but interlocking nature of these companies may provide legal buffering but also makes it difficult to get clear answers about the services they sell and success rates. On its website (before taking it down last week), IFG claimed that 54% of all IVF cycles done with MRT have resulted in pregnancy. When asked to substantiate that claim, IFG said that data came from its partner clinics and that medical teams there have to verify it before sharing. Kal and his wife, Ozlem, who operates the SAGA Clinic, where most of IFG’s clients have gone to receive MRT, told STAT that they don’t collect such data, because they have no ability to follow up with patients after they leave the SAGA facilities. “Our collaboration with IFG is akin to a leasing arrangement,” Ozlem Kal said in an email. “IFG manages and plans the care for its patients — utilizing its own teams and operating entirely under the leadership of Dr. Uliana — from the beginning of the procedure to the end.” IFG clients told STAT that they also sought more detailed data from the company that could give them a better sense of their own chances, and were repeatedly ignored. “Direct questions about success rates and outcomes were met with extreme defensiveness, confusing and incomplete answers, or outright evasion,” said one current IFG client who asked for anonymity out of fear of retribution from the company. In her experience, she said, other fertility doctors emphasized fully informing patients with statistics relevant to their age groups. “This has felt like a fundamental part of their code of ethics,” she said. “At IFG, it was the complete opposite.” Pasha Itsykson, a prominent embryologist in Israel, told STAT he was stunned by IFG’s results when he was approached by the company about referring patients to its MRT program — so much so that he found academic collaborators willing to raise money to run a formal trial and help publish the data IFG had already collected. But when those academics offered to fly to Albania to see all the documentation, they were turned away. “They didn’t want to share any data,” Itsykson said. Aydin and Dorofeyeva also declined to provide additional data to STAT explaining the 54% pregnancy rate claim. “I’m not a responsible person for the website, so I cannot really comment there,” Dorofeyeva said. In interviews, both she and Aydin distanced themselves from IFG’s more aggressive marketing to women of advanced maternal age. “We never said that MRT will change the euploidy rate or solve the problem of aging,” Dorofeyeva said. Becoming “the people of MRT, that was never our intention.” To hear them tell it, after seeing potential in their first few clinical case studies of MRT in Ukraine, they would have been happy to continue to offer it slowly and quietly to patients at a handful of fertility clinics in Europe. But then IFG got involved, opening up the U.S. market, and things got out of control. “We became very overloaded,” Dorofeyeva said. Aydin said he had refused about 80% of patients applying for IFG’s mitochondrial donation program. But patients would push back, even after he explained to them there might be no direct benefit. “Before going to egg donation or deciding that they will not have a child anymore or that they will adopt, they want to try their last chance,” he said. “So I mean, how can you say ‘no’?” With the swelling demand came inflated expectations. Aydin said he was soon overwhelmed by the near-constant messaging from IFG clients, some of whom shared their anxieties about the financial stress of pursuing MRT — which increased when IFG raised the cost of its package earlier this year from $20,000 to $30,000 — or got angry when they didn’t get desired results. “They were sharing everything with me,” he said. “I started to feel more disturbed.” At the end of July — after STAT’s visit to the company headquarters and the story in Nature critical of some of IFG’s claims — the company placed a banner at the top of its webpage announcing that enrollment of new patients for its mitochondrial donation program was temporarily on pause. Existing clients were told that the last treatment group was to take place in October, according to company communications obtained by STAT. After that, IFG could not guarantee women who’d begun banking eggs for MRT would be able to finish what they started. That’s because Aydin has, for now, decided to take a break from performing MRT. Being stretched so thin started to wear on his health, he told STAT, and he no longer thinks patients should be paying for an experimental treatment for which it is so difficult to select the patients who may benefit. For her part, Dorofeyeva said she doesn’t plan to pursue MRT for her patients with other clinics or embryologists. “I wouldn’t say I believe in the technology; I believe in the technology in Birol’s hands,” she said. “I’m not a commercial person,” she added. A network diagram illustrates some of the overlapping corporate and familial connections between business entities and individuals involved in mitochondrial donation. ‘Everyone is scrambling’ The news of IFG pausing its MRT program sent shockwaves of panic, anger, and confusion among those who’d already paid for the program and those who had been hoping to get in. Many existing clients began rushing to move their eggs and embryos to Albania or arrange last-minute retrievals. “Everyone is scrambling for it because they want it so bad,” said one IFG client who asked for anonymity to protect her privacy and out of fear of retaliation from the company. Some hopeful clients took up IFG’s offer to secure a priority waitlist spot with a $1,000 deposit. Others urgently sought information about alternatives. But even in just the last few months, that information has become harder to find. Two clinics in the Philippines with connections to Aydin — IVF Asia Group and Fertility Philippines — previously advertised MRT on their websites, referring to the procedure as “oocyte rejuvenation.” Women 40 and above could have a live birth rate of 60% for each embryo transferred, IVF Asia Group’s website stated, while a page on Fertility Philippines’ website claimed the technology “effectively rewinds your biological clock, offering success rates comparable to those of a 30-year-old woman.” Both pages and all references to oocyte rejuvenation were removed over the summer. Reached by text, Kent McQueen, the clinics’ chief executive, said the embryologist who performed the MRT procedures had left and they’re still trying to replace him. IFG is also trying to hire someone to reboot its MRT program, STAT has learned. In October, the company reached out to Mazur with an offer to pick up where Aydin left off, this time at a clinic in the Dominican Republic. Mazur said he declined. Uncertainty about whether clinics are truly closing, or just moving underground, might mean fewer patients being drawn in and potentially taken advantage of. However, bioethicists told STAT it’s a complicated tradeoff because it would also mean even less transparency into these human experiments going forward. “We’d like to know if this actually works, because if it does then actually we should be licensing it more broadly and we might consider removing our current appropriations rider that blocks FDA from considering this technology,” said I. Glenn Cohen, director of Harvard Law School’s Petrie-Flom Center for Health Law Policy, who has studied MRT and medical tourism and believes there need to be well-controlled clinical trials. Patients told STAT they would prefer to be a part of a clinical trial that could provide concrete evidence that MRT is both safe and effective. But they’re not willing to wait for one to materialize. Not when time is their enemy. A few years ago, an American doctor named Zaher Merhi opened an outpost of his U.S.-based clinic franchise Rejuvenating Fertility Center in the Bahamas, where he recently started to offer a different form of MRT, involving transferring genetic material from immature eggs. So far, the clinic has attempted to reconstruct embryos for just two patients, only one successfully. That patient has not yet attempted a transfer. Despite the lack of data on the new procedure, Merhi said his waiting list is long and growing longer every day. He’s currently hiring more doctors to support the influx of demand. Are you pursuing MRT as a treatment for infertility? STAT wants to hear from you *Required Are you someone who has or is currently pursuing MRT as a treatment for infertility? Or are you a physician or researcher with information about fertility clinics offering MRT outside the U.S.? We are looking to speak with those familiar with how such clinics operate, including how they advertise the risks and benefits of the procedure to potential patients. If that’s you, please fill out the form below to share your experiences with STAT reporter Megan Molteni. We will not use your information or your name in a story without first communicating with you and getting your permission. Edward Chen, a freelance writer and former intern at STAT, contributed to this story from the U.S., and Inva Hasanaliaj contributed reporting from Albania. STAT’s coverage of bioethics is supported by a grant from the Greenwall Foundation and the Boston Foundation. Our financial supporters are not involved in any decisions about our journalism. About the Author Reprints Megan Molteni Science Writer Megan covers the intersection of science and society. How is biomedical research funded? Who benefits? And how do new technologies reflect and shape our values? You can reach Megan on Signal at mmolteni.13. To submit a correction request, please visit our Contact Us page.
Women travel thousands of miles for a reproductive moonshot. Scientists say they’ve been misled
Full Article
Original Source
Read the full article at Statnews →KhanList aggregates and links to publicly available news content. We do not host full articles from third-party sources. Always verify important information with original sources.